Emergency Dentist Care for Cracked Molars and Biting Pain
A cracked molar rarely announces itself with drama at first. More often, it starts as a sharp twinge when you chew on one side, a brief zing with cold water, or a vague sense that something feels "off" when your teeth come together. Patients often tell me they thought it was a seed stuck in the gum, sinus pressure, or sensitivity from whitening toothpaste. Then they bite into toast, a nut, or even a soft sandwich, and the pain turns specific, immediate, and impossible to ignore.
This is where emergency dental care matters. A cracked molar can move from manageable to serious in a matter of days, sometimes hours, depending on the depth and direction of the fracture. The reason biting pain is so revealing is that chewing places force directly through the crack. When the tooth flexes microscopically, the inner structures become irritated. If the crack reaches the pulp, where the nerve and blood supply live, pain can escalate quickly and infection becomes a real concern.
Not every cracked molar needs the same treatment, and not every biting pain means the tooth is doomed. But when a back tooth hurts under pressure, especially if that pain feels sharp on release, it deserves prompt attention from an Emergency Dentist.
Why molars crack so often
Molars do hard labor. They absorb the heaviest forces in the mouth, often hundreds of pounds of pressure in people who clench or grind. Their broad chewing surfaces make them efficient, but also vulnerable. Deep grooves, old fillings, repeated stress, and sudden force all raise the risk of cracking.
A common pattern goes like this: a patient has a large filling placed years ago, maybe after a cavity in a lower first molar. Over time, the remaining tooth structure weakens. Add nightly grinding, a habit of chewing ice, or one unlucky bite on an olive pit, and the tooth develops a fracture line. Sometimes the crack starts so small it cannot be seen easily on a routine glance. The pain gives it away before the eye does.
Age plays a role too. Teeth become less flexible over time. That does not mean cracking is inevitable, only that a 50-year-old molar with a large restoration has usually been through more than a healthy 20-year-old molar with untouched enamel.
The kind of pain that points toward a crack
Cracked molars have a distinctive pain pattern, though not always a perfect one. The classic complaint is pain when biting down or, even more suggestive, pain when releasing Emergency Dentist pressure. Patients often say, "It hurts when I let go." That detail matters. As the tooth compresses and springs back, the crack can momentarily open and irritate the pulp or surrounding dentin.
Temperature sensitivity is also common, especially to cold. Hot sensitivity can be more concerning because it sometimes points to deeper nerve inflammation. Not all cracked teeth react the same way, though. Some barely notice temperature but flare during chewing. Others throb spontaneously, a sign the crack may have extended far enough to inflame or infect the pulp.
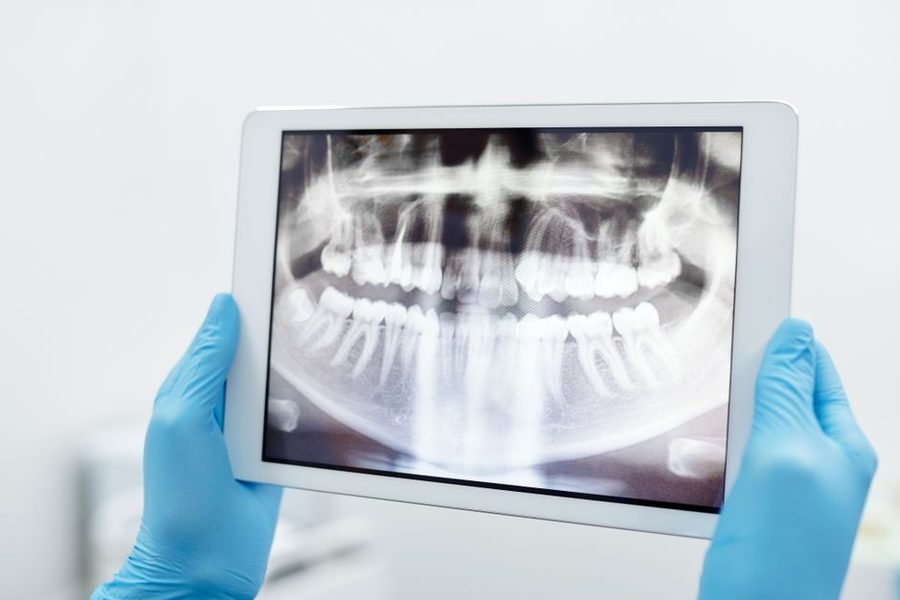
Biting pain in a molar can come from other causes, including a high filling, a cavity, a periodontal problem, a vertical root fracture, or even referred pain from another tooth. That is why self-diagnosis is unreliable. A proper emergency dental exam usually includes a focused history, bite testing, percussion, thermal testing, and dental X-rays. In some cases, magnification and transillumination help reveal the fracture.
What counts as a dental emergency
A cracked molar with mild symptoms still deserves quick evaluation, but certain signs push it firmly into emergency territory. Severe pain, visible swelling, a bad taste from drainage, fever, difficulty opening the mouth, or pain that wakes you at night should not wait. A tooth that has split enough for part of the crown to move can deteriorate fast. Infection around the tooth or under the gum can spread and become much harder to treat if ignored.
The reason many offices reserve same-day or next-day slots for these cases is simple. The earlier the tooth is stabilized, the better the chance of preserving it. A tooth with a fresh crack may be saved with a bonded restoration or crown. The same tooth, after days of repeated chewing and bacterial leakage, may end up needing root canal therapy or extraction.
If you are deciding whether to call an Emergency Dentist, the safest rule is practical: if chewing hurts enough that you are avoiding that side, the tooth is sensitive to cold or heat in a new way, or the pain is worsening, call.
What to do before your appointment
There is a narrow but useful window between noticing the problem and getting into the chair. During that time, your main job is to avoid turning a crack into a split.
Use the opposite side for chewing. Stay away from hard, crunchy, sticky, or very chewy foods. Nuts, crusty bread, candy, jerky, and ice are all bad bets. Keep the area clean with gentle brushing and warm salt water rinses if the gum feels irritated. If the tooth is sensitive, avoid very cold drinks and extremely hot foods. Over-the-counter pain relievers may help if you can take them safely, but they should not be used to postpone care when the pain is significant.
One mistake I see often is people "testing" the tooth every few hours to see if it still hurts. That repeated pressure can worsen the fracture. Another is using temporary filling material from a pharmacy when the issue is not a missing filling but a structural crack. Those products may help cover a rough area, but they do not brace a weakened molar against chewing forces.
What an Emergency Dentist is looking for
The emergency visit is not only about stopping pain in the moment. It is about figuring out whether the tooth is restorable and what level of intervention will protect it long term. Diagnosis can be tricky because cracks do not always show clearly on X-rays. A fracture running through the crown may be invisible unless the pieces have separated.
Dentists usually rely on a combination of clues. Bite tests can localize the painful cusp. A tooth slooth or similar instrument lets the patient bite on individual cusps one at a time. If one cusp reproduces the pain, that narrows the problem. Transillumination can make a crack line stand out. Periodontal probing helps check whether the crack has extended below the gumline, which affects prognosis. If the pulp is inflamed but still alive, there may be a path to save the tooth with a crown. If the pulp has become irreversibly inflamed or infected, root canal therapy may be added to the plan.
There are judgment calls involved. A superficial craze line on a front tooth often needs nothing. A cracked molar with Emergency Dentist pain under load is different. Molars do not get much forgiveness once structural integrity is compromised.
The treatments that are most commonly used
Treatment depends on how deep the crack goes, whether the nerve is involved, and whether the tooth can be predictably restored. There is no one-size-fits-all answer, and honest dentists will say so.
Here are the options most often considered:
- Protective bonded restoration or onlay for a limited crack where enough healthy tooth remains and the pulp looks stable.
- Full-coverage crown when the tooth needs bracing against chewing forces, which is common for cracked molars.
- Root canal therapy plus crown if the crack has irritated or infected the pulp but the root structure remains restorable.
- Extraction if the crack extends too far below the gumline, splits the tooth, or creates a hopeless prognosis.
- Temporary stabilization in an emergency visit, followed by definitive treatment once pain is controlled and the diagnosis is confirmed.
Patients sometimes ask why a crown is so often recommended instead of "just a filling." The answer is biomechanics. A filling replaces missing material. A crown helps hold the cusps together and reduces flexing under load. For a cracked molar, that bracing effect can be the difference between a tooth that settles down and a tooth that keeps failing.
When a crown helps, and when it is not enough
There is a stage in cracked tooth treatment where timing matters enormously. If the crack is confined mostly to the crown and the pulp is irritated but not irreversibly damaged, placing a crown can protect the tooth and stop the pain from biting. I have seen teeth go from "I cannot chew oatmeal on that side" to comfortable function after proper coverage and adjustment.
But a crown is not magic. If the pulp is already badly inflamed, the symptoms may persist even after the tooth is covered. That is why some patients need root canal treatment before or after crown placement. The sequence depends on how the tooth tests, how severe the symptoms are, and whether there is evidence of irreversible pulpitis or infection. Good emergency care is not guesswork, but it does require clinical judgment because cracked teeth can evolve.
A particularly difficult scenario is the crack that tracks into the root. These teeth may present with a narrow, isolated deep periodontal pocket near the fracture. Sometimes the pain is inconsistent, which misleads people into waiting. Once a vertical root fracture is confirmed, the long-term outlook is poor, and extraction becomes the most realistic option.
The signs that a crack may be deeper than expected
No single symptom proves a hopeless fracture, but certain patterns make dentists more cautious. Pain that is severe, lingering, and spontaneous is more likely to involve the pulp. Swelling or a pimple-like bump on the gum suggests infection. A piece of tooth that moves independently is a bad sign. Deep gum probing beside one root can point to a crack extending downward.
This is one area where online advice often causes confusion. People read that "if it only hurts when biting, it is minor" or "if cold bothers it, it can still be saved." Sometimes those statements are true. Sometimes they are not. I have seen teeth with modest symptoms that split dramatically a week later, and I have seen painful cracked molars recover well once they were stabilized quickly. Symptoms help, but they do not replace an exam.
How dentists decide whether the tooth is worth saving
Patients deserve a straight answer about prognosis, cost, and the likely treatment path. Saving a cracked molar often makes sense because natural teeth usually chew better and preserve bone more naturally than replacements. But that does not mean every molar should be rescued at any cost.
The decision often comes down to three questions. First, where is the crack? A crack confined above the gumline carries a very different outlook from one running down the root. Second, can the tooth be predictably restored? Even if the pain can be controlled, there has to be enough healthy structure left for a durable restoration. Third, what is the condition of the surrounding tooth and gum support? A heavily restored tooth with bone loss, recurrent decay, and a deep fracture may not be a wise candidate for complex treatment.
A good Emergency Dentist will also factor in the patient's reality. Someone with limited time before travel, a history of heavy grinding, or financial constraints may need a different sequence of care than someone who can move directly into definitive treatment. Pragmatism matters. The best plan is the one that is both clinically sound and actually achievable.
Cost, urgency, and the mistake of waiting for it to "settle"
Many dental pains do fluctuate. A cracked tooth may hurt sharply for two days, then quiet down enough to create false confidence. That does not necessarily mean the problem is improving. Sometimes it means the pulp is transitioning from irritation to deeper damage. By the time swelling starts, the treatment path is usually more involved.
From a cost standpoint, early care is often less expensive than delayed care. A crown is generally less invasive and less costly than root canal therapy plus crown. Both are usually preferable, financially and biologically, to extraction followed by an implant or bridge. Prices vary by region and practice, so broad numbers can be misleading, but the pattern is consistent: the earlier a restorable crack is stabilized, the better the odds of a simpler bill and a simpler recovery.
What recovery usually feels like
After emergency treatment, the tooth may remain tender for a few days, especially if the surrounding ligament has been inflamed by biting trauma. That is not unusual. What dentists want to see is a trend toward improvement, not escalation. Chewing comfort should gradually return. Temperature sensitivity should lessen or at least not intensify.
If a temporary band, sedative filling, or provisional crown is placed, the tooth still needs protection until final treatment is completed. This is where patients can accidentally sabotage good care by going back to normal eating too soon. A temporary restoration is not meant to survive caramel, almonds, or a steakhouse challenge. Follow-through matters as much as the emergency visit itself.
How to reduce the chance of another cracked molar
Cracks are not always preventable, but risk can be lowered with a few practical habits. The first is dealing with grinding or clenching. Many adults are unaware they do it until a dentist points out wear facets, scalloped tongue edges, or fractured restorations. A properly made night guard does not make a tooth invincible, but it can significantly reduce repeated stress.
The second is respecting restored teeth. Molars with large fillings are often strong enough for daily function, but they are not ideal candidates for chewing ice, cracking shellfish, or opening packages. The third is not postponing routine care when a filling is breaking down. Small structural problems become larger ones under years of chewing.
A short preventive checklist is worth keeping in mind:
- Wear a night guard if you clench or grind.
- Avoid chewing ice, popcorn kernels, and other hard objects.
- Repair leaking or broken fillings before the tooth weakens further.
- Get biting pain evaluated early, especially in a back tooth.
- Finish recommended crown treatment if a dentist says the tooth needs bracing.
A common real-world scenario
Consider a patient in her mid-40s who feels a sharp jab in a lower molar while eating granola. The pain fades quickly, so she ignores it. Over the next week, cold water starts to sting, and biting on that side feels wrong, though not unbearable. She takes smaller bites and chews around it. On the tenth day, she bites into a soft sandwich, feels a sudden electric shock, and then notices a dull ache for hours.
At the emergency visit, the tooth has an older, wide filling. One cusp is painful on bite release, and the cold test lingers a bit longer than normal. The X-ray is not dramatic, but the exam strongly suggests a cracked tooth. Because the tooth is still restorable, it is stabilized and scheduled for definitive full coverage. If she had come earlier, the path might have been even simpler. If she had waited until swelling developed, root canal therapy or extraction might have entered the picture. That gap, often just days or weeks, is where outcomes change.
Choosing the right help when pain starts
When people search online for relief, they often focus on getting through the night. That is understandable, but the better question is who can diagnose and stabilize the problem correctly. For cracked molars and biting pain, the right call is usually an Emergency Dentist who can examine the tooth promptly, take appropriate images, and either provide definitive care or guide the next step without delay.
Urgency does not mean panic. It means recognizing that back teeth under pain from chewing are sending useful information. Teeth do not flex and hurt for no reason. If a molar is cracked, the clock does not run in your favor while you continue to chew on it.
A cracked tooth caught early can often be saved and returned to comfortable function. A cracked tooth ignored long enough can become a much larger problem, biologically and financially. When biting pain is new, specific, and tied to a molar, prompt evaluation is the smart move.
Smyle Dental Bakersfield
2016 E St, Bakersfield, CA 93301, United States
+16614939040
FAQ About Emergency Dentist
What counts as a dental emergency?
Severe tooth pain, facial swelling, uncontrolled bleeding, a knocked-out or displaced tooth, and significant dental trauma may need prompt assessment. Trouble breathing or rapidly increasing swelling requires urgent medical help.
What should I do if a permanent tooth is knocked out?
Handle the tooth by the crown rather than the root, keep it moist, and contact a dentist immediately. Fast treatment can improve the chance of saving the tooth.
Can an emergency dentist treat severe tooth pain the same day?
Same-day care may be available depending on the cause and schedule. The dentist will examine the area, may take digital X-rays, and recommend treatment based on the diagnosis.
Should I go to the emergency room for dental swelling?
Seek urgent medical care for trouble breathing, difficulty swallowing, rapidly spreading facial swelling, or other severe symptoms. A dentist can assess the underlying dental cause and provide appropriate follow-up care.